Evaluating and Understanding Model Editing for Medical Vision-Language Models
M3Bench: a clinically grounded benchmark for evaluating reliability, locality, generality, compositionality, modality shift, and temporal consistency in medical VLM model editing.
Overview
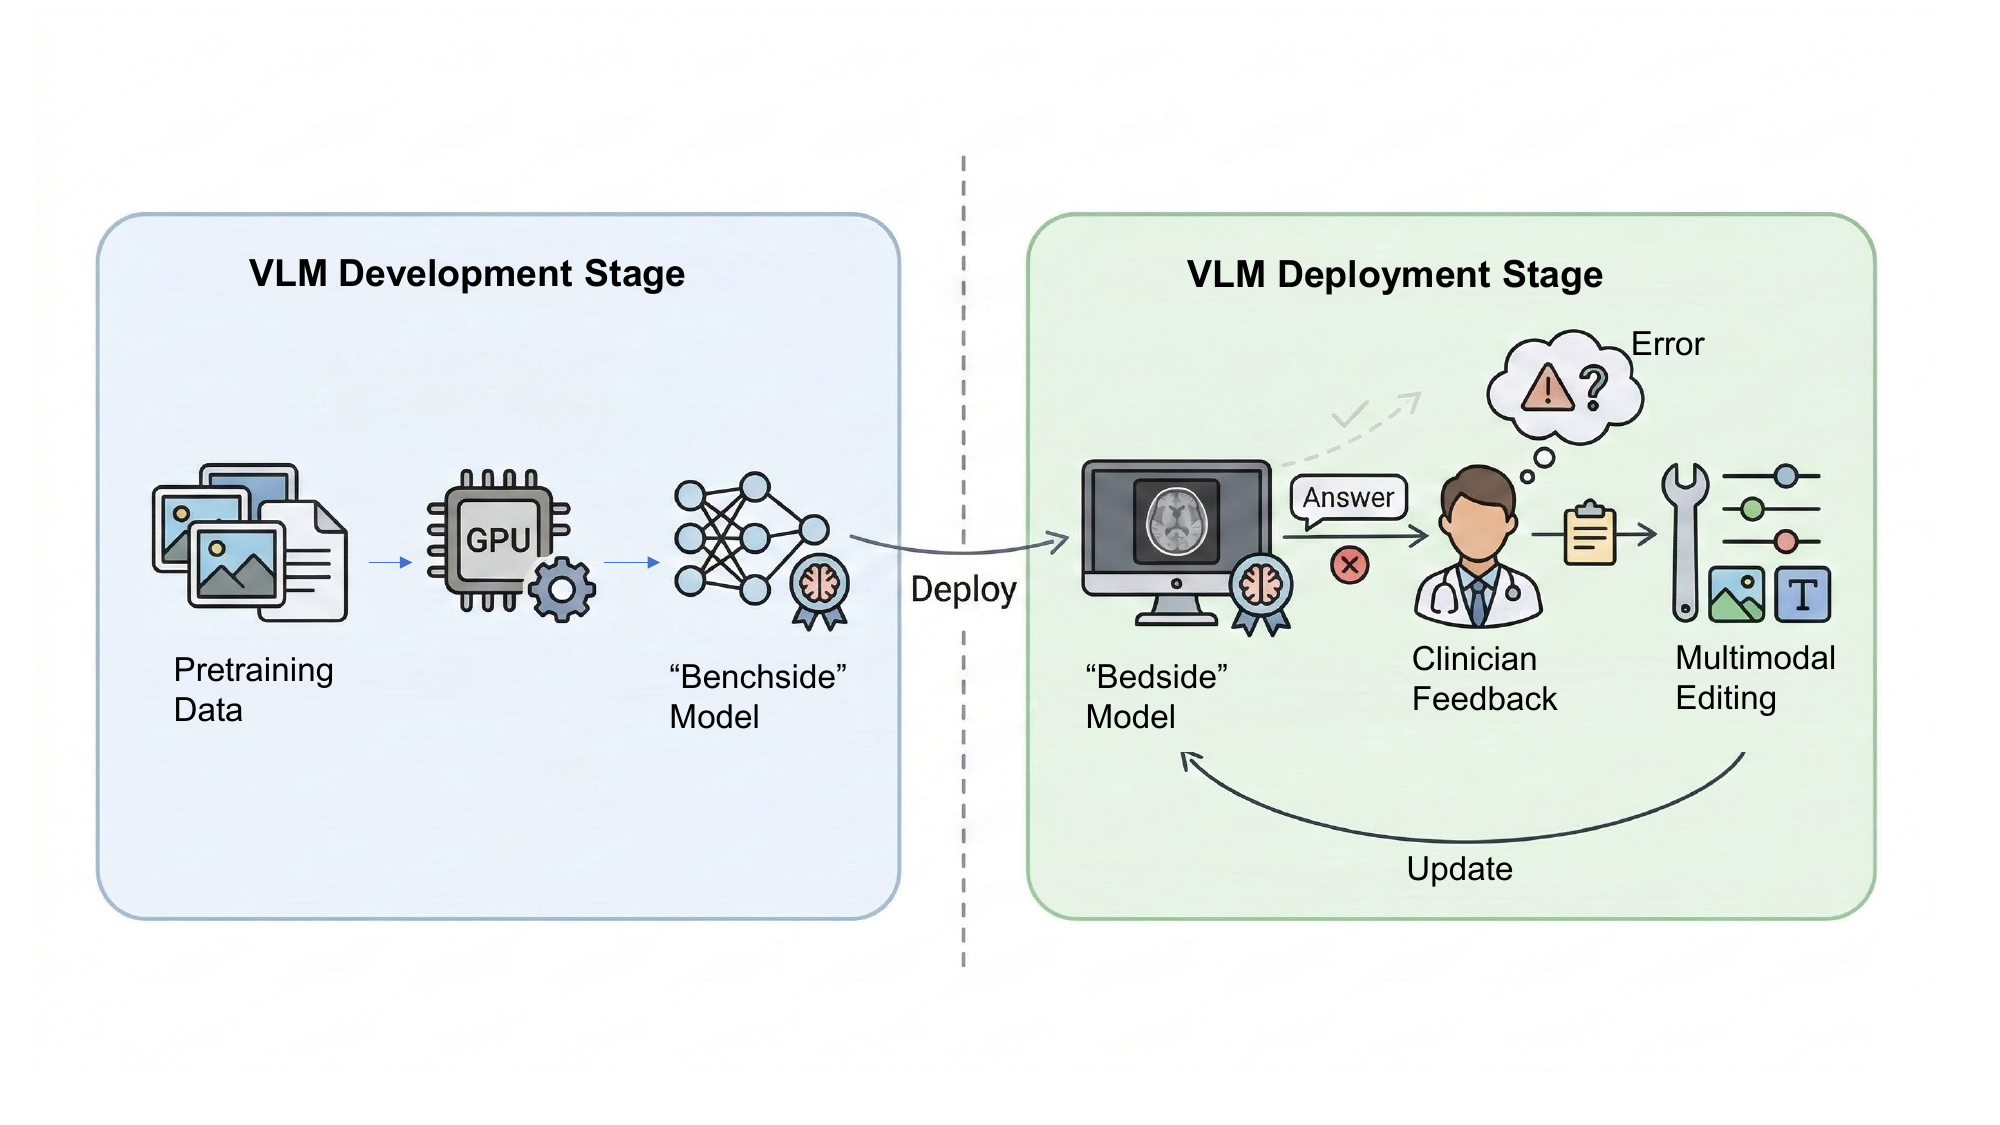
Medical vision-language models are increasingly used for image-grounded clinical reasoning, but post-deployment failures are inevitable due to distribution shifts, changing protocols, rare findings, and patient-specific variation. Model editing offers a lightweight way to correct targeted mistakes without full retraining. However, existing editing benchmarks are often too simplified for clinical deployment.
M3Bench evaluates whether an edit is not only successful on the target error, but also precise, clinically transferable, robust to multimodal variation, and consistent across related clinical contexts.
Benchmark Design
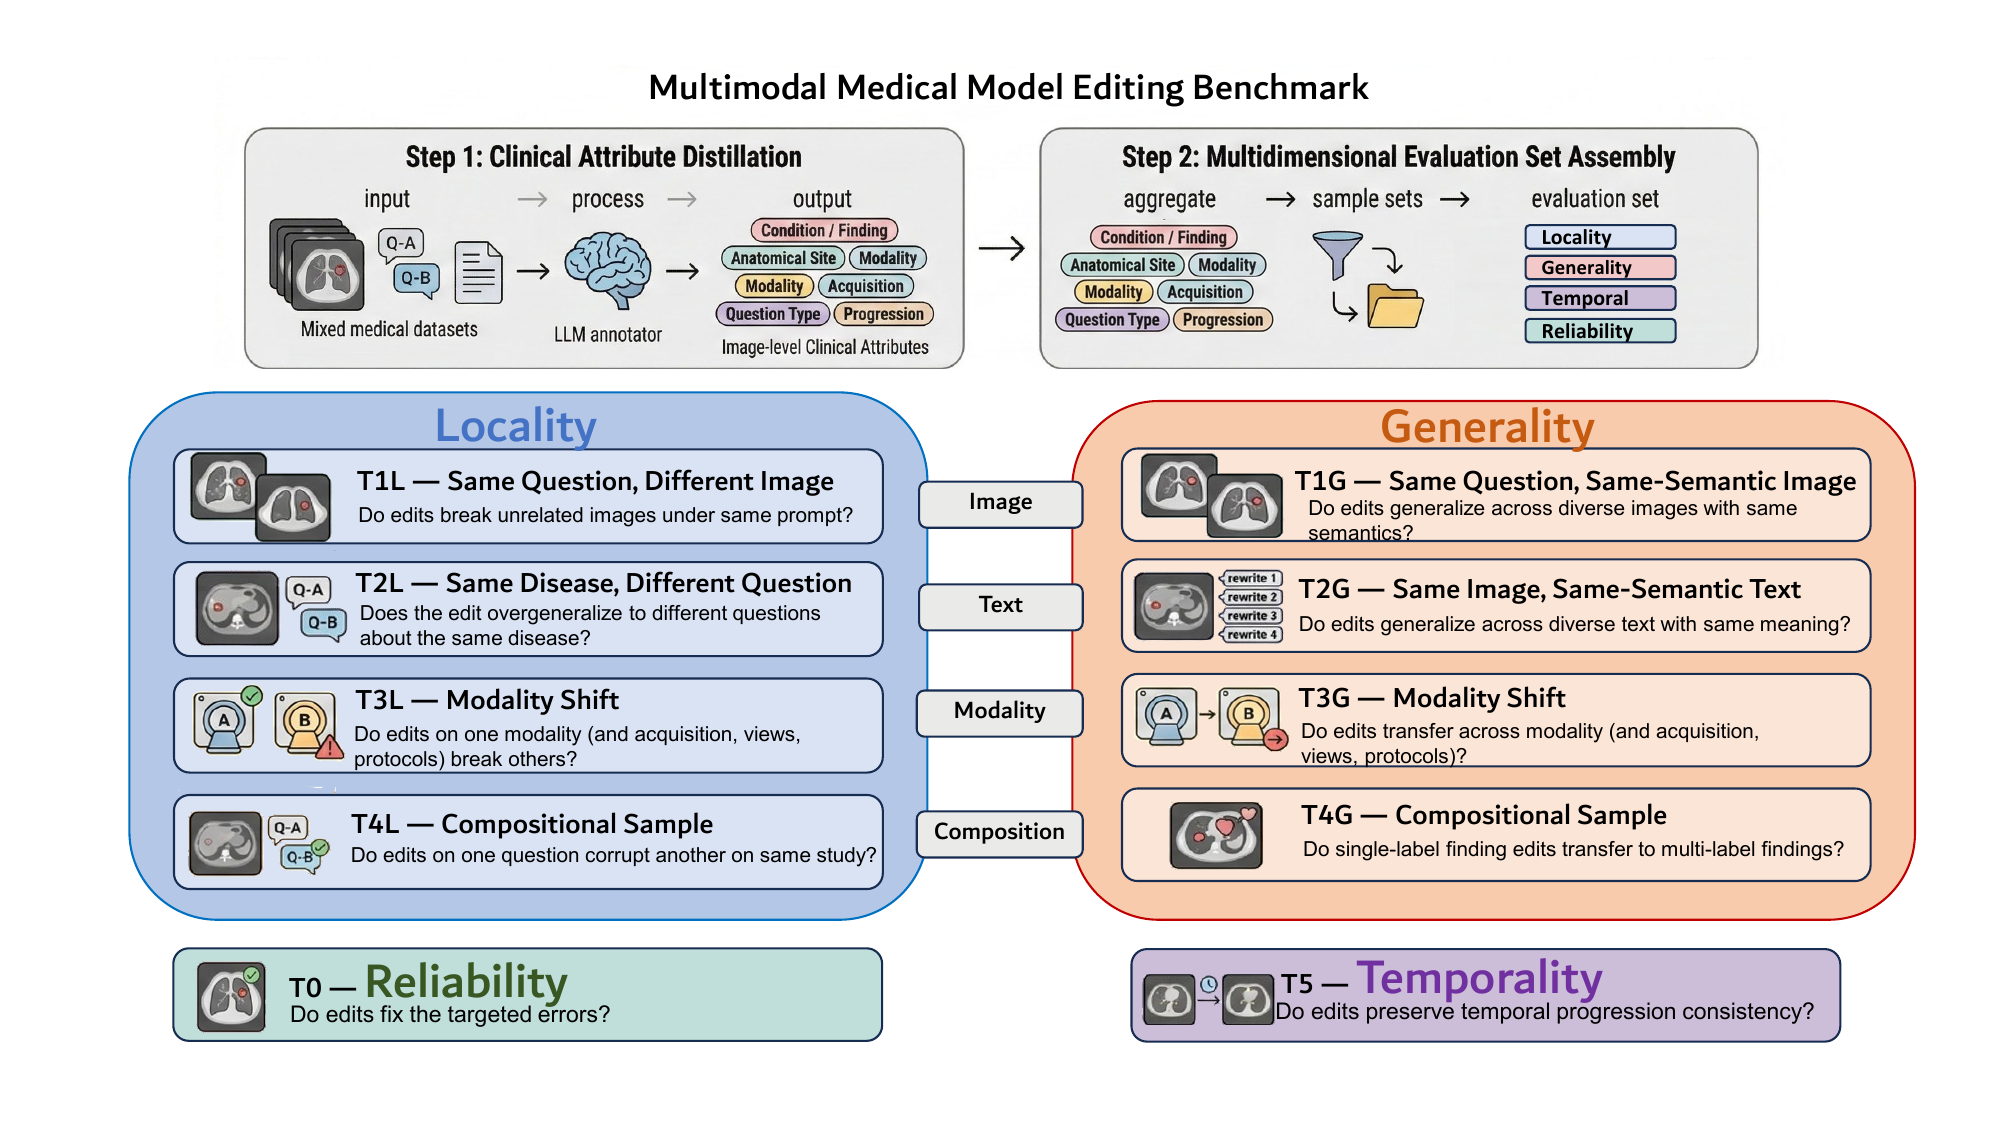
M3Bench is organized around three core editing desiderata: Reliability, Locality, and Generality. We extend these criteria into clinically meaningful settings involving image variation, text variation, modality and protocol shifts, clinical composition, and longitudinal temporal consistency.
Reliability
Tests whether an edit corrects the originally observed model failure on the target image-question pair.
Locality
Tests whether the edit preserves previously correct behavior on unrelated or non-target clinical concepts.
Generality
Tests whether the edit transfers to clinically equivalent variants, such as new patient images, paraphrased questions, or matched cases under modality shift.
Temporal Consistency
Tests whether an edit remains coherent across longitudinal prior-follow-up studies where disease progression or resolution matters.
Task Suite
| Task | Evaluation Goal |
|---|---|
| T0 Reliability | Correct the original target error. |
| T1L Image Locality | Same question, unrelated images. The edit should not become prompt-only or image-agnostic. |
| T1G Image Generality | Same question, semantically matched images. The edit should transfer to similar patient cases. |
| T2L Text Locality | Same image, different clinical question. The edit should preserve other correct answers. |
| T2G Text Generality | Same image, semantic-preserving rewrites. The edit should handle paraphrases and clinical phrasing variation. |
| T3L/T3G Modality Shift | Evaluate preservation and transfer across scanner, protocol, view, or modality changes. |
| T4L/T4G Clinical Composition | Evaluate editing behavior when multiple findings co-occur in the same clinical case. |
| T5 Temporal Consistency | Evaluate whether edits remain coherent across prior and follow-up studies. |
Dataset Composition
M3Bench is built from public medical VQA and image-text resources, including VQA-RAD, SLAKE, PMC-VQA, and PadChest-GR. The benchmark contains 16,276 questions over 1,398 unique images, covering multiple imaging modalities, anatomical sites, and clinical findings.
Original third-party images and datasets are not redistributed. The release provides processed benchmark metadata and instructions for reconstructing the benchmark after obtaining the source datasets.
Experimental Setup
We evaluate four representative medical VLM backbones and four model editing methods.
Medical VLMs
LLaVA-Med BioMed-Qwen HuatuoGPT-Vision 7B HuatuoGPT-Vision 34B
Editing Methods
MEND GRACE BalancEdit LoRA
We group editing methods into two families: gradient-based editors, such as MEND and LoRA, and memory-based editors, such as GRACE and BalancEdit. The benchmark evaluates both single-edit and sequential-edit settings.
Main Results
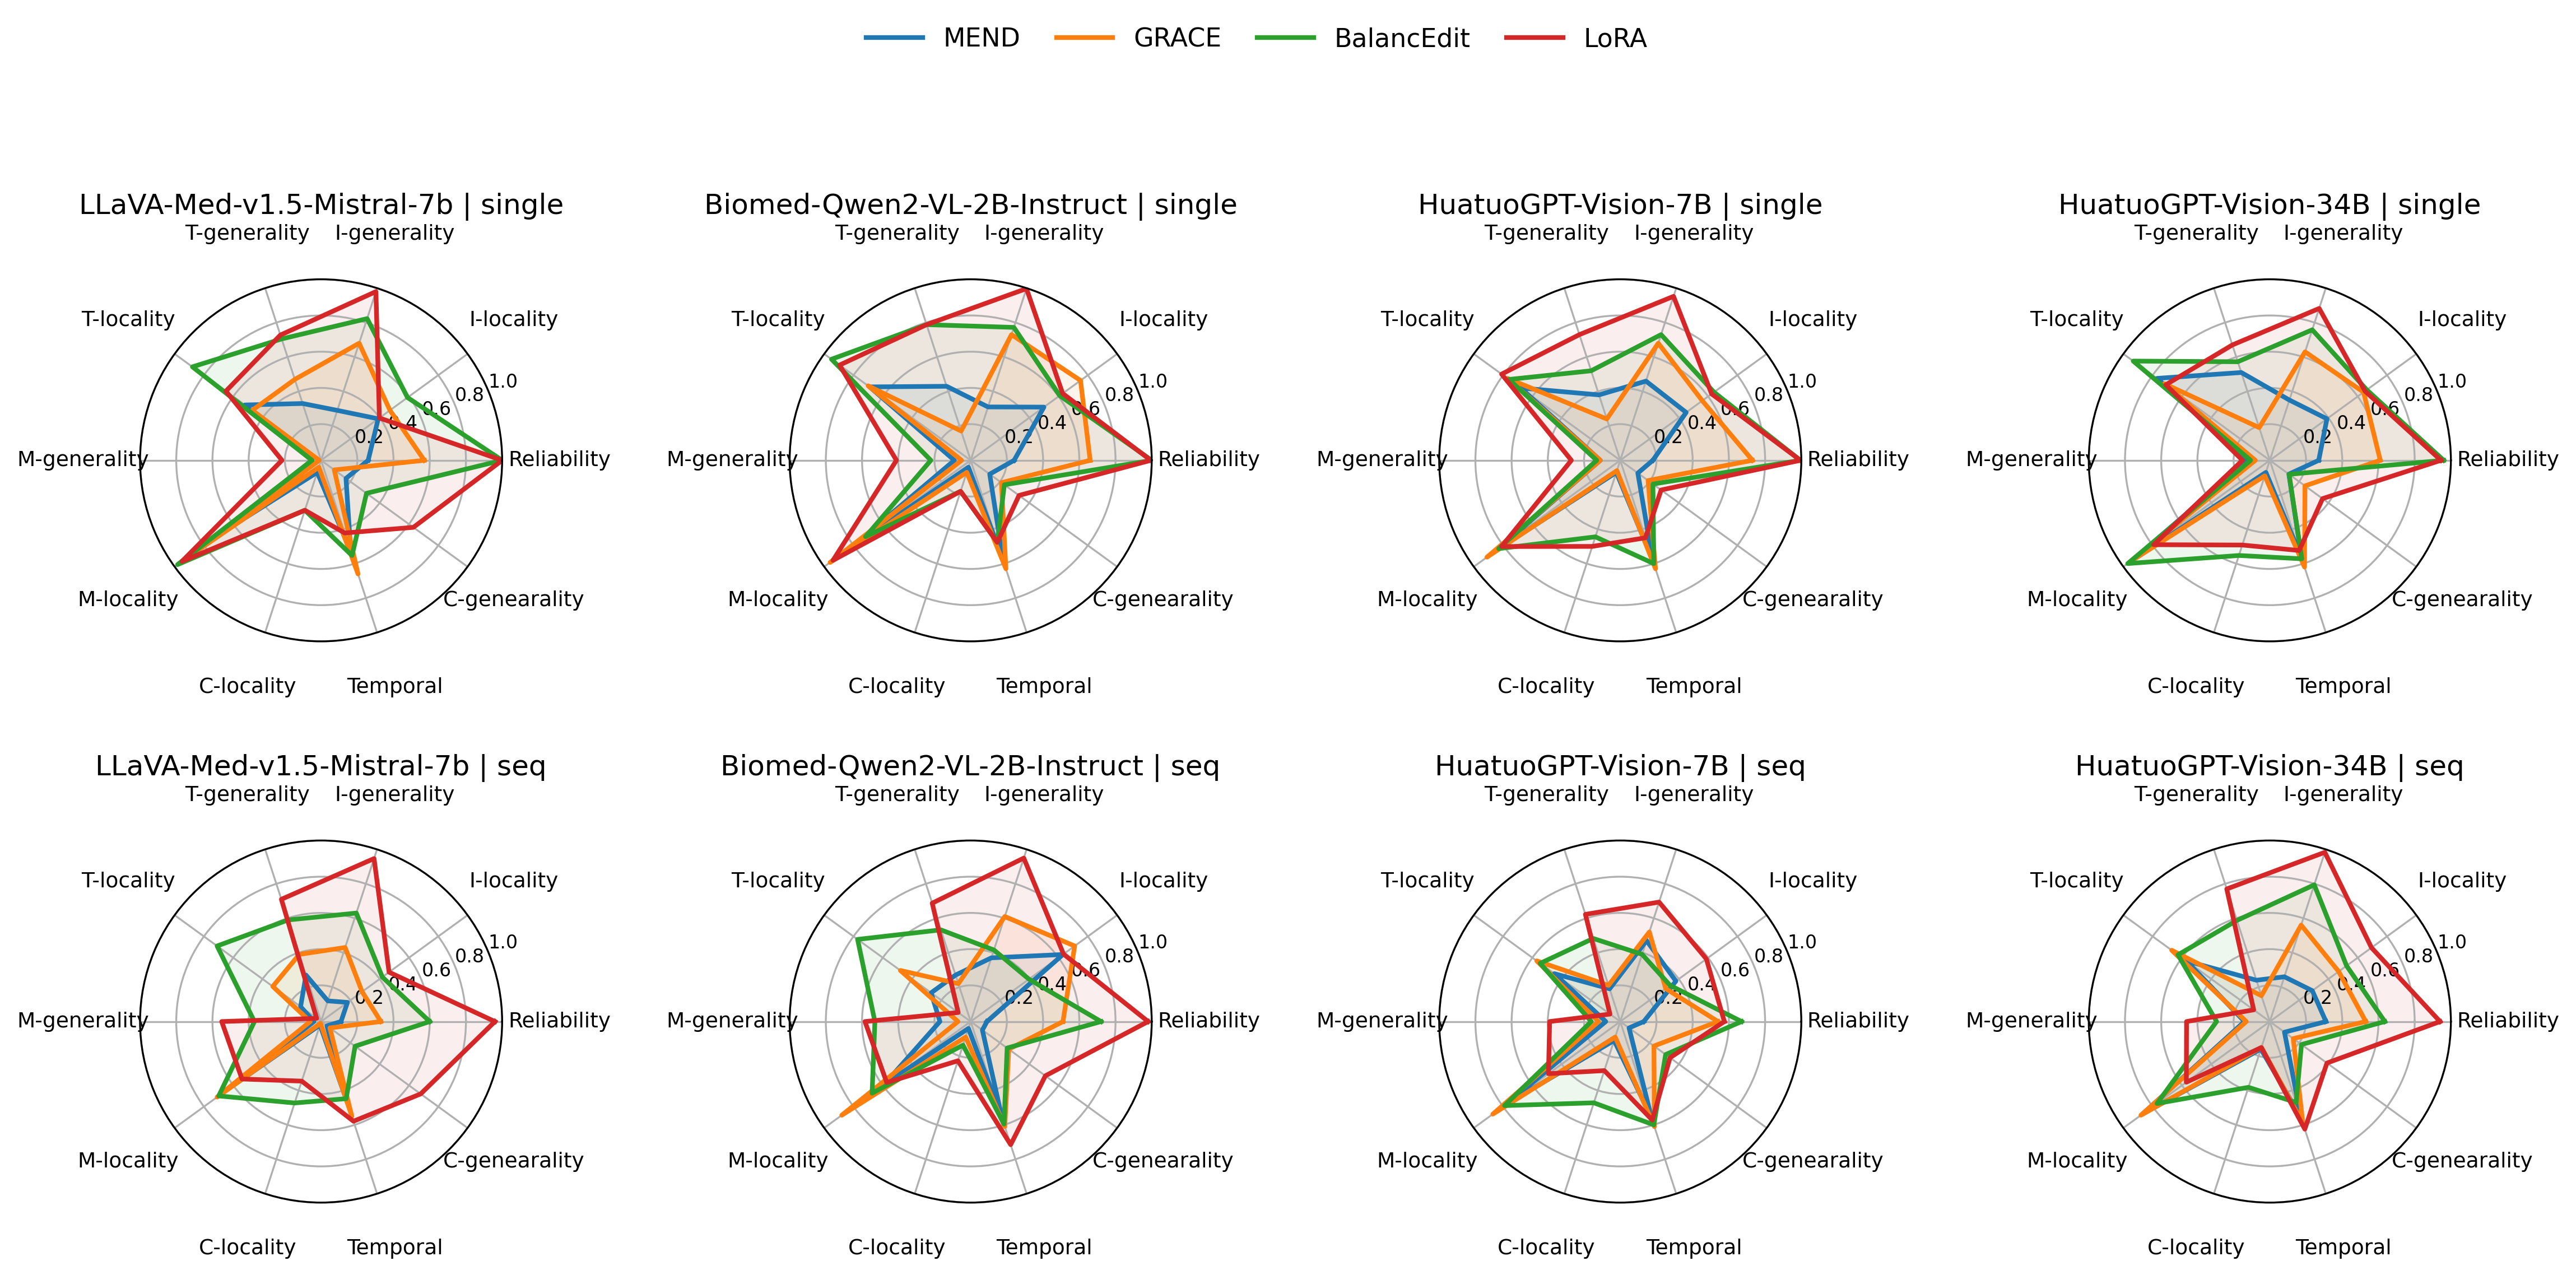
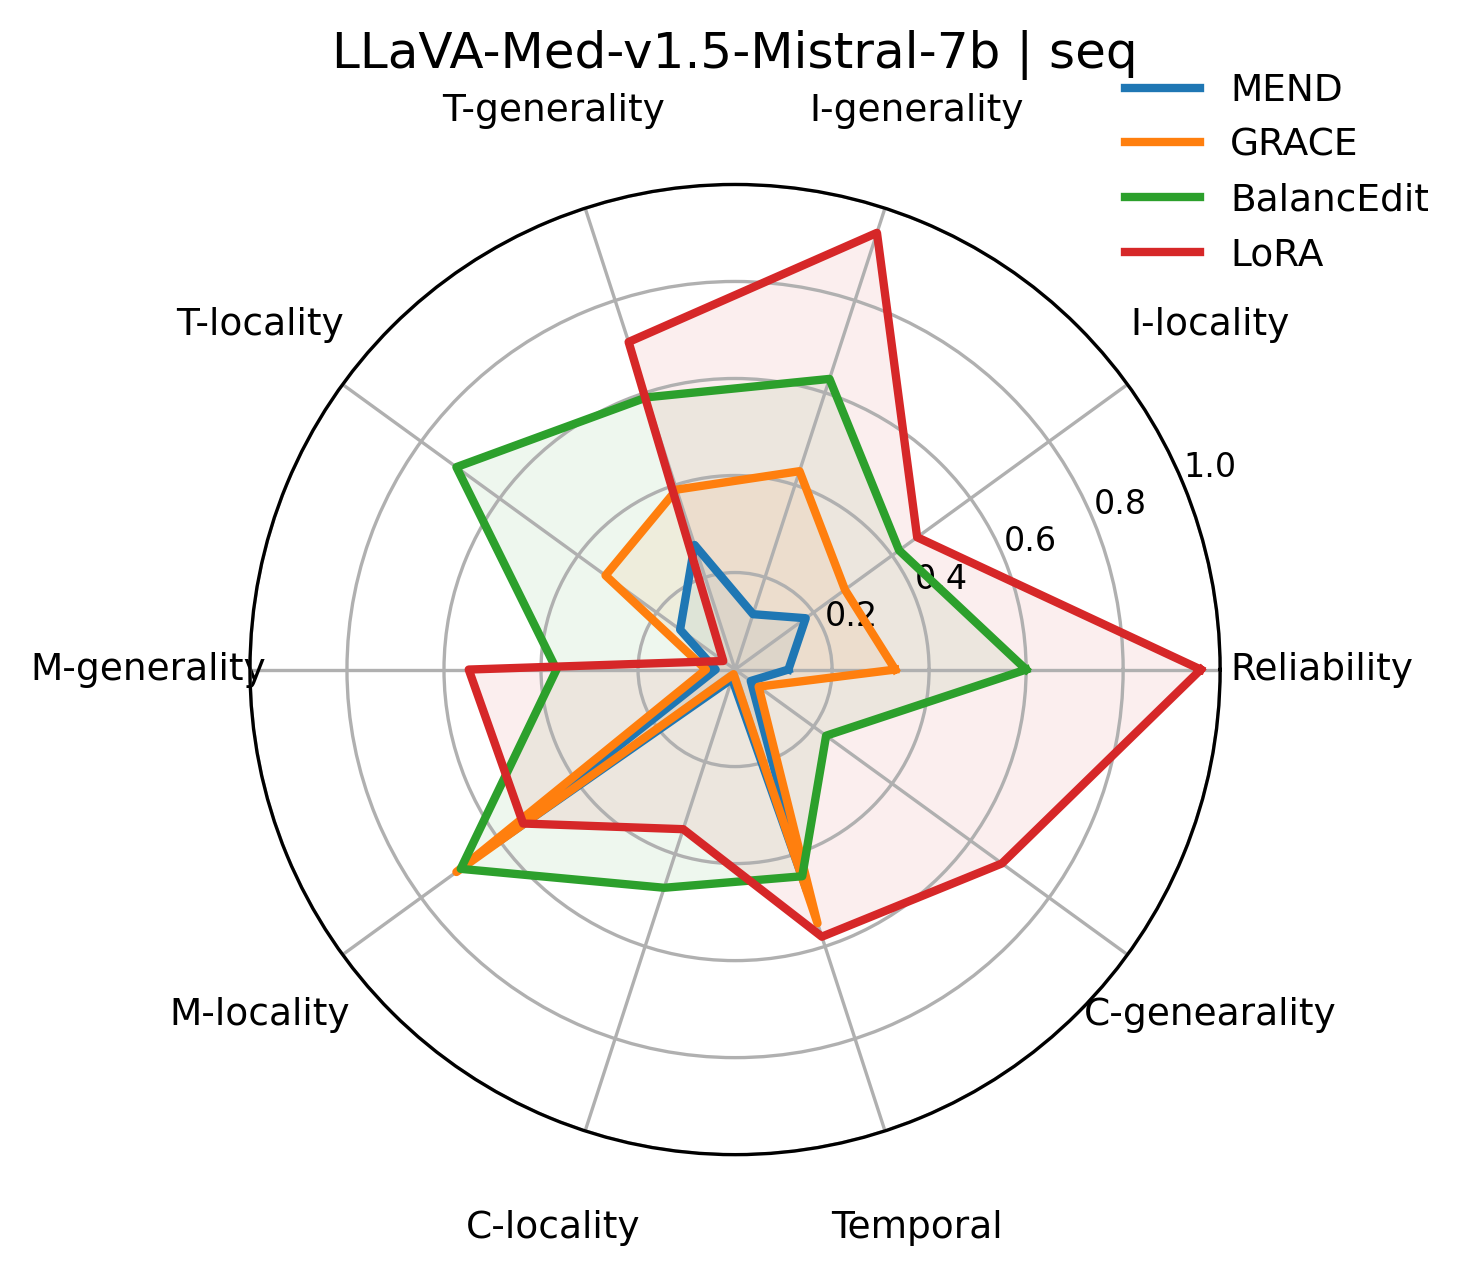
Across models and tasks, no single editing method dominates all clinical criteria. Gradient-based editors often achieve strong reliability and generality, but can cause serious locality failures. Memory-based editors better preserve locality, but struggle with compositional transfer and require careful hyperparameter calibration.
Key Findings
LoRA
Achieves strong reliability and broad generality, but can collapse locality under clinically plausible non-target probes.
BalancEdit
Provides the most balanced performance in many settings, but remains sensitive to radius calibration and struggles with composition and temporality.
GRACE
Preserves locality better than broad gradient updates, but often lacks sufficient transfer to semantically related clinical cases.
MEND
Offers efficient learned updates, but is less stable under the multimodal clinical stress tests used in M3Bench.
Analysis
Representation Geometry
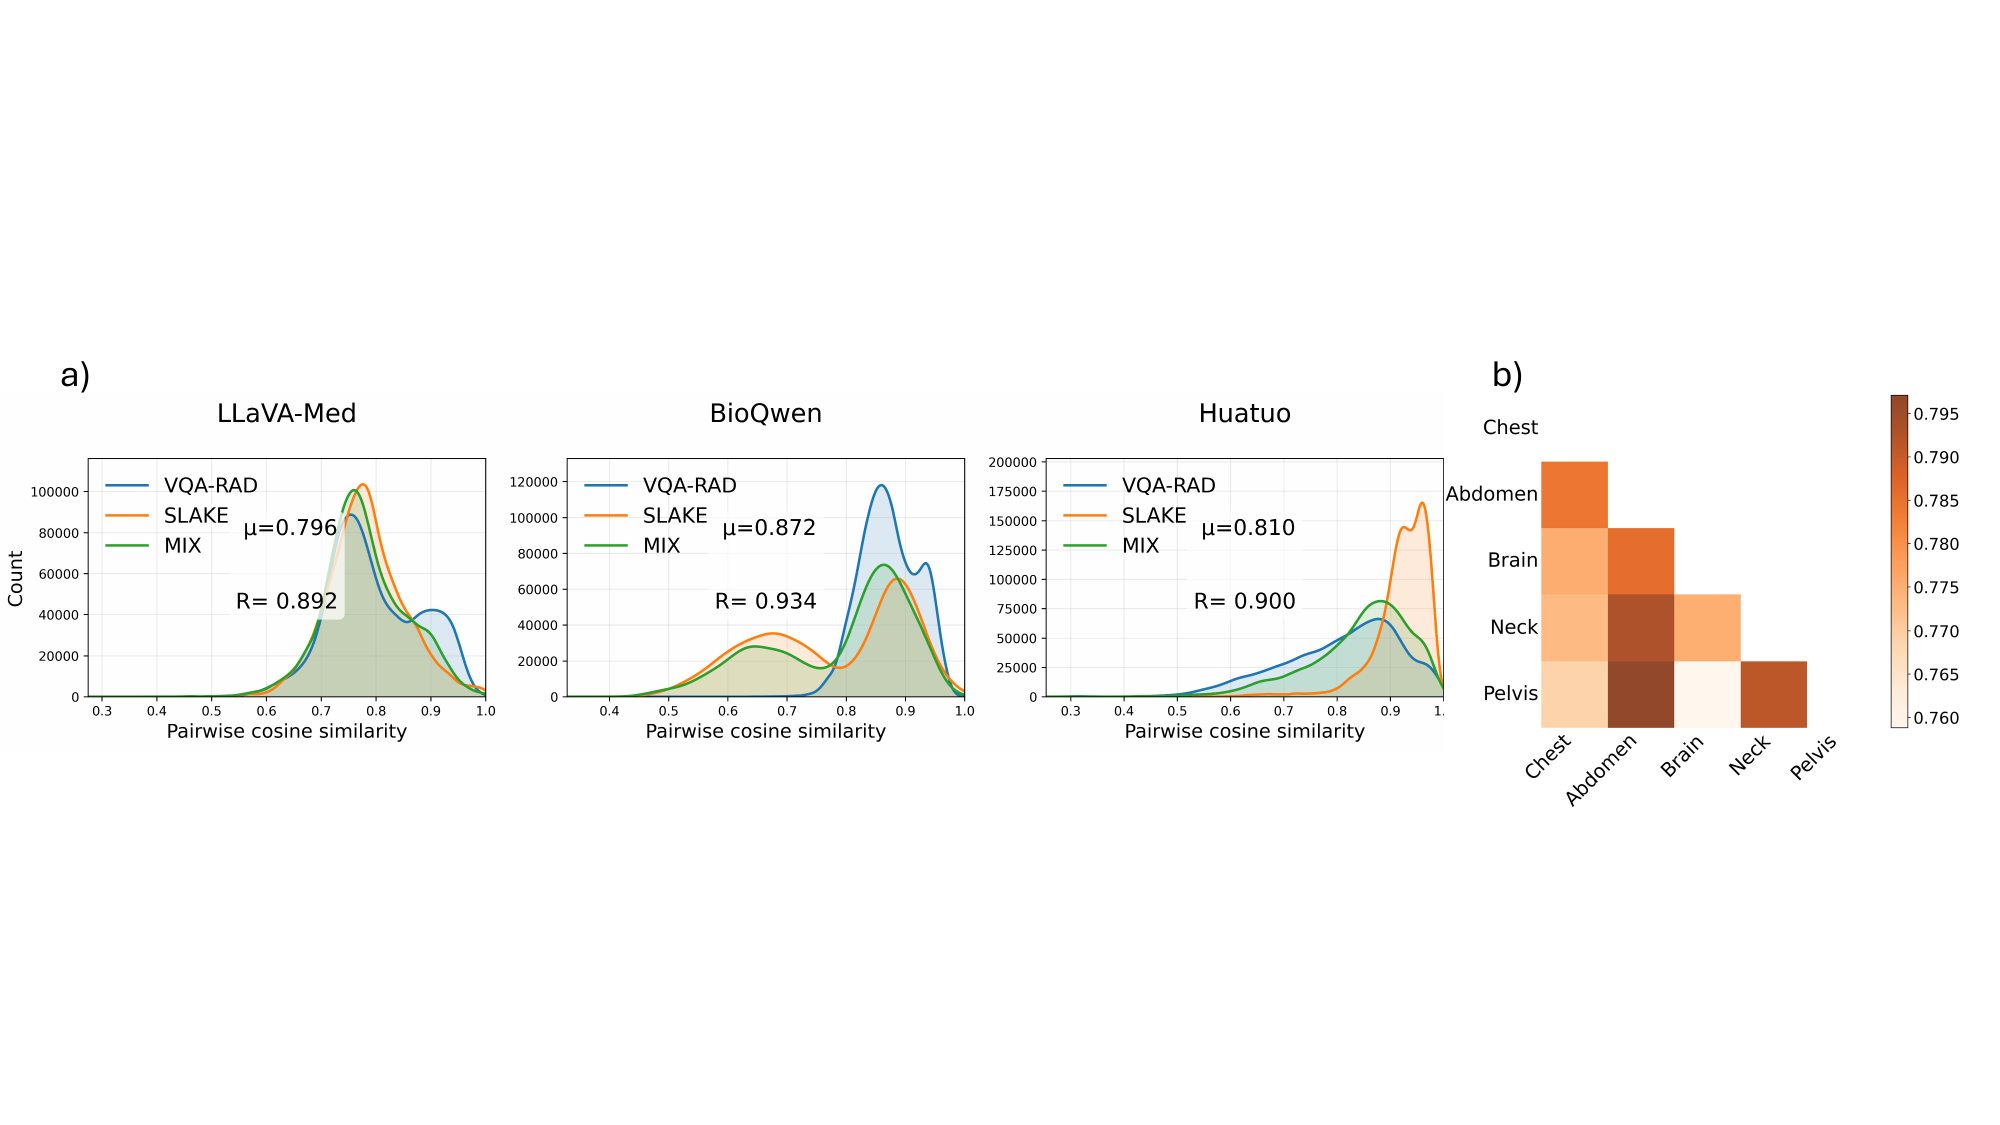
We analyze medical VLM latent representations and find that embeddings are highly anisotropic: medical concepts concentrate in a narrow cone. This makes localized editing difficult because nearby clinical concepts can be unintentionally affected by a targeted update.
Non-target Concept Drift
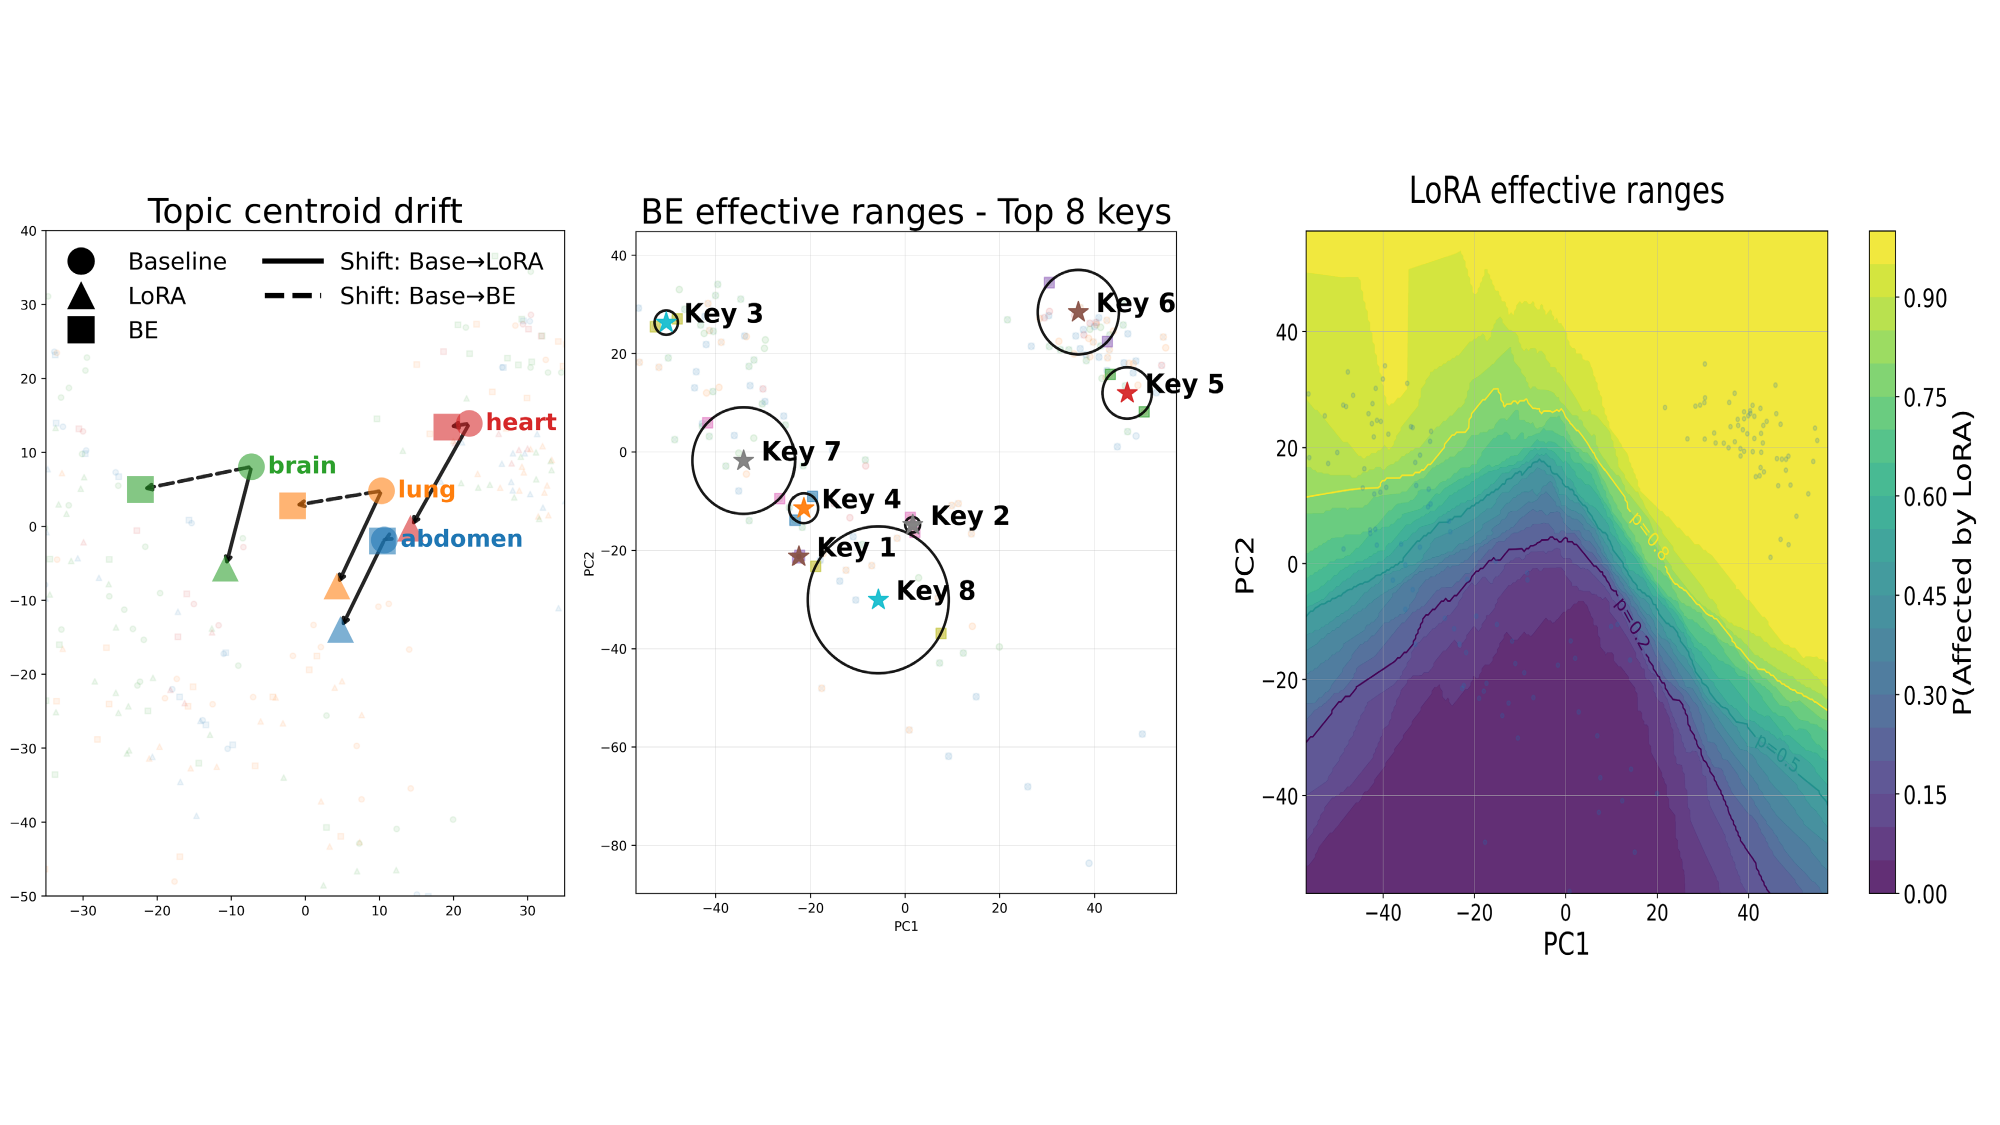
Gradient-based editors tend to induce broader latent-space shifts, which can move non-target clinical concepts and cause locality failures. Memory-based editors restrict activation to a gated region, which improves locality but may limit transfer.
Compositional Failure Modes
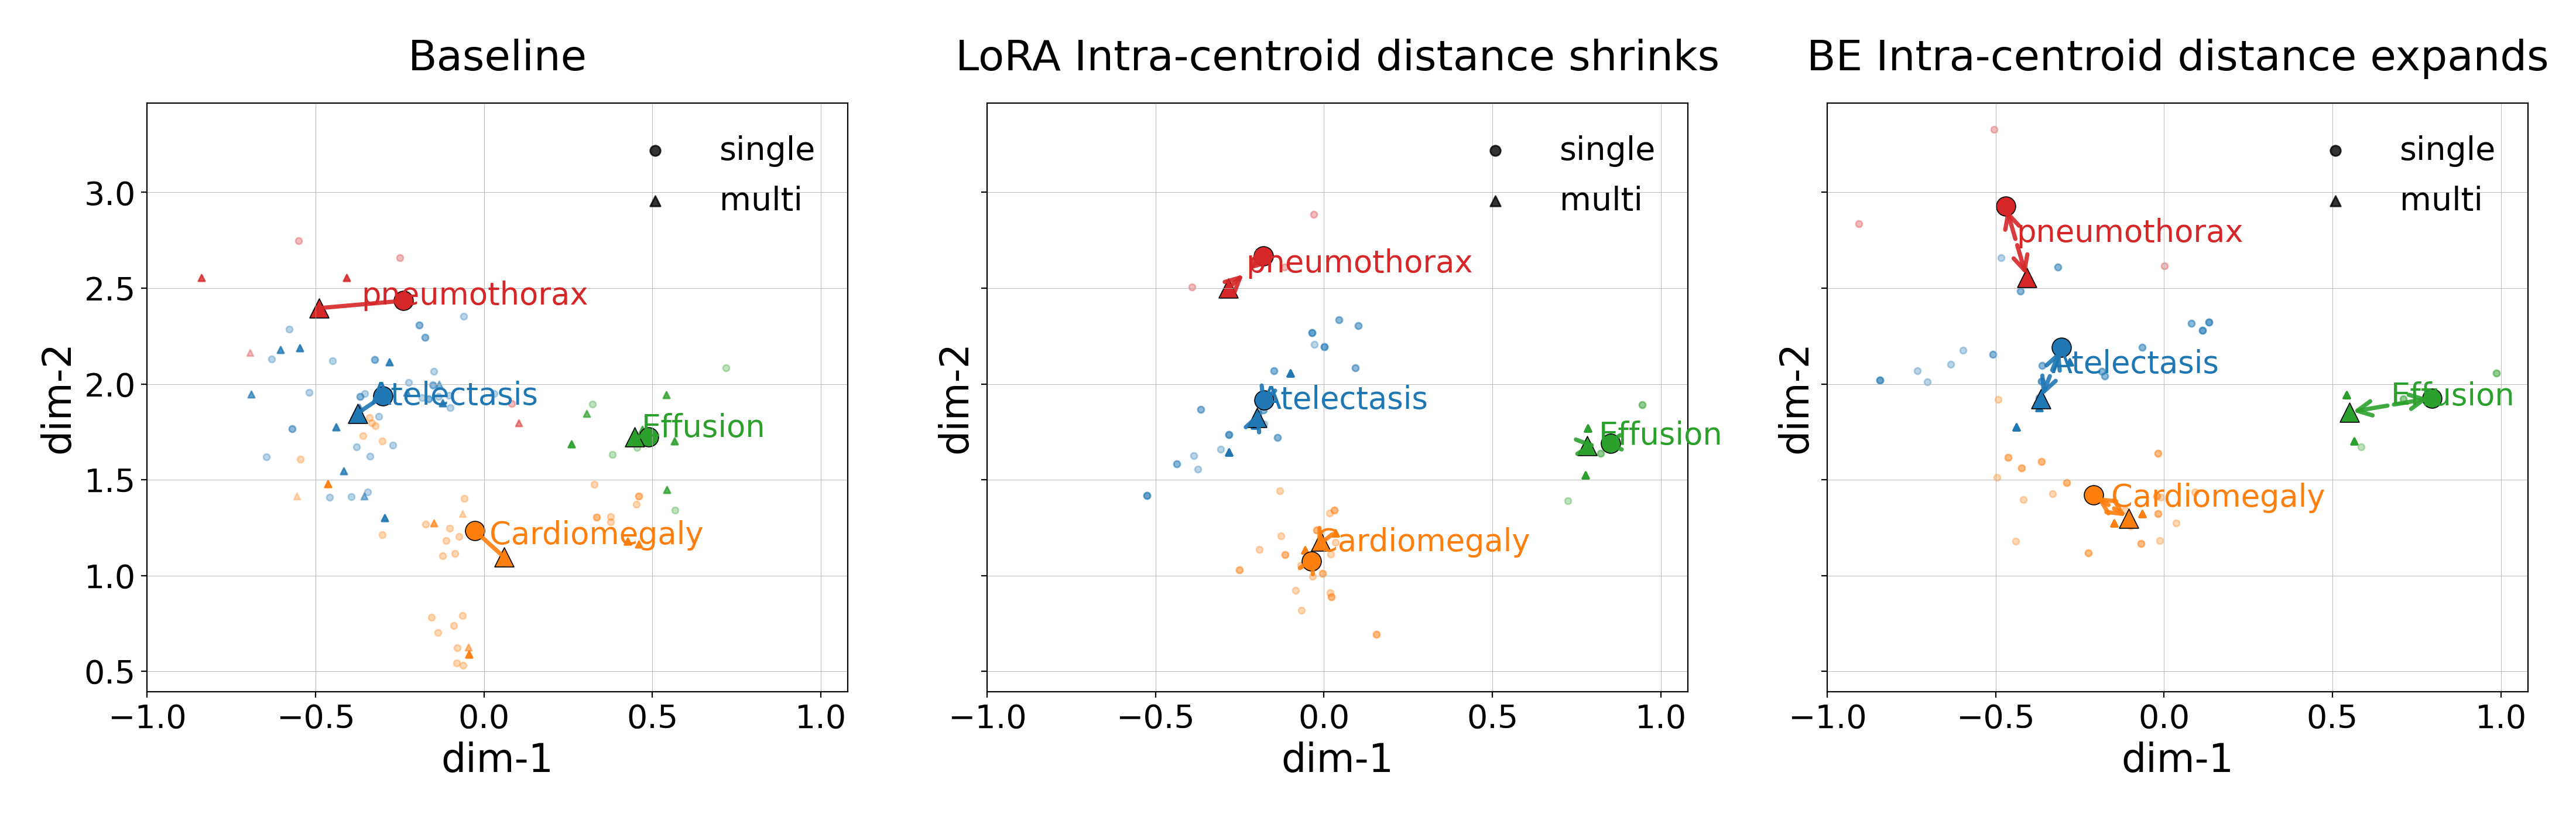
Clinical cases often contain multiple co-occurring findings. Memory-based editors can under-transfer from single-finding edits to multi-finding cases because hard activation boundaries may not capture partially overlapping clinical evidence.
Where to Edit
We further study component and layer sensitivity using a hybrid BELoRA editor. Editing the language model together with the vision-language projector provides useful gains, while expanding to the vision encoder does not consistently improve stability.
Hyperparameter Sensitivity
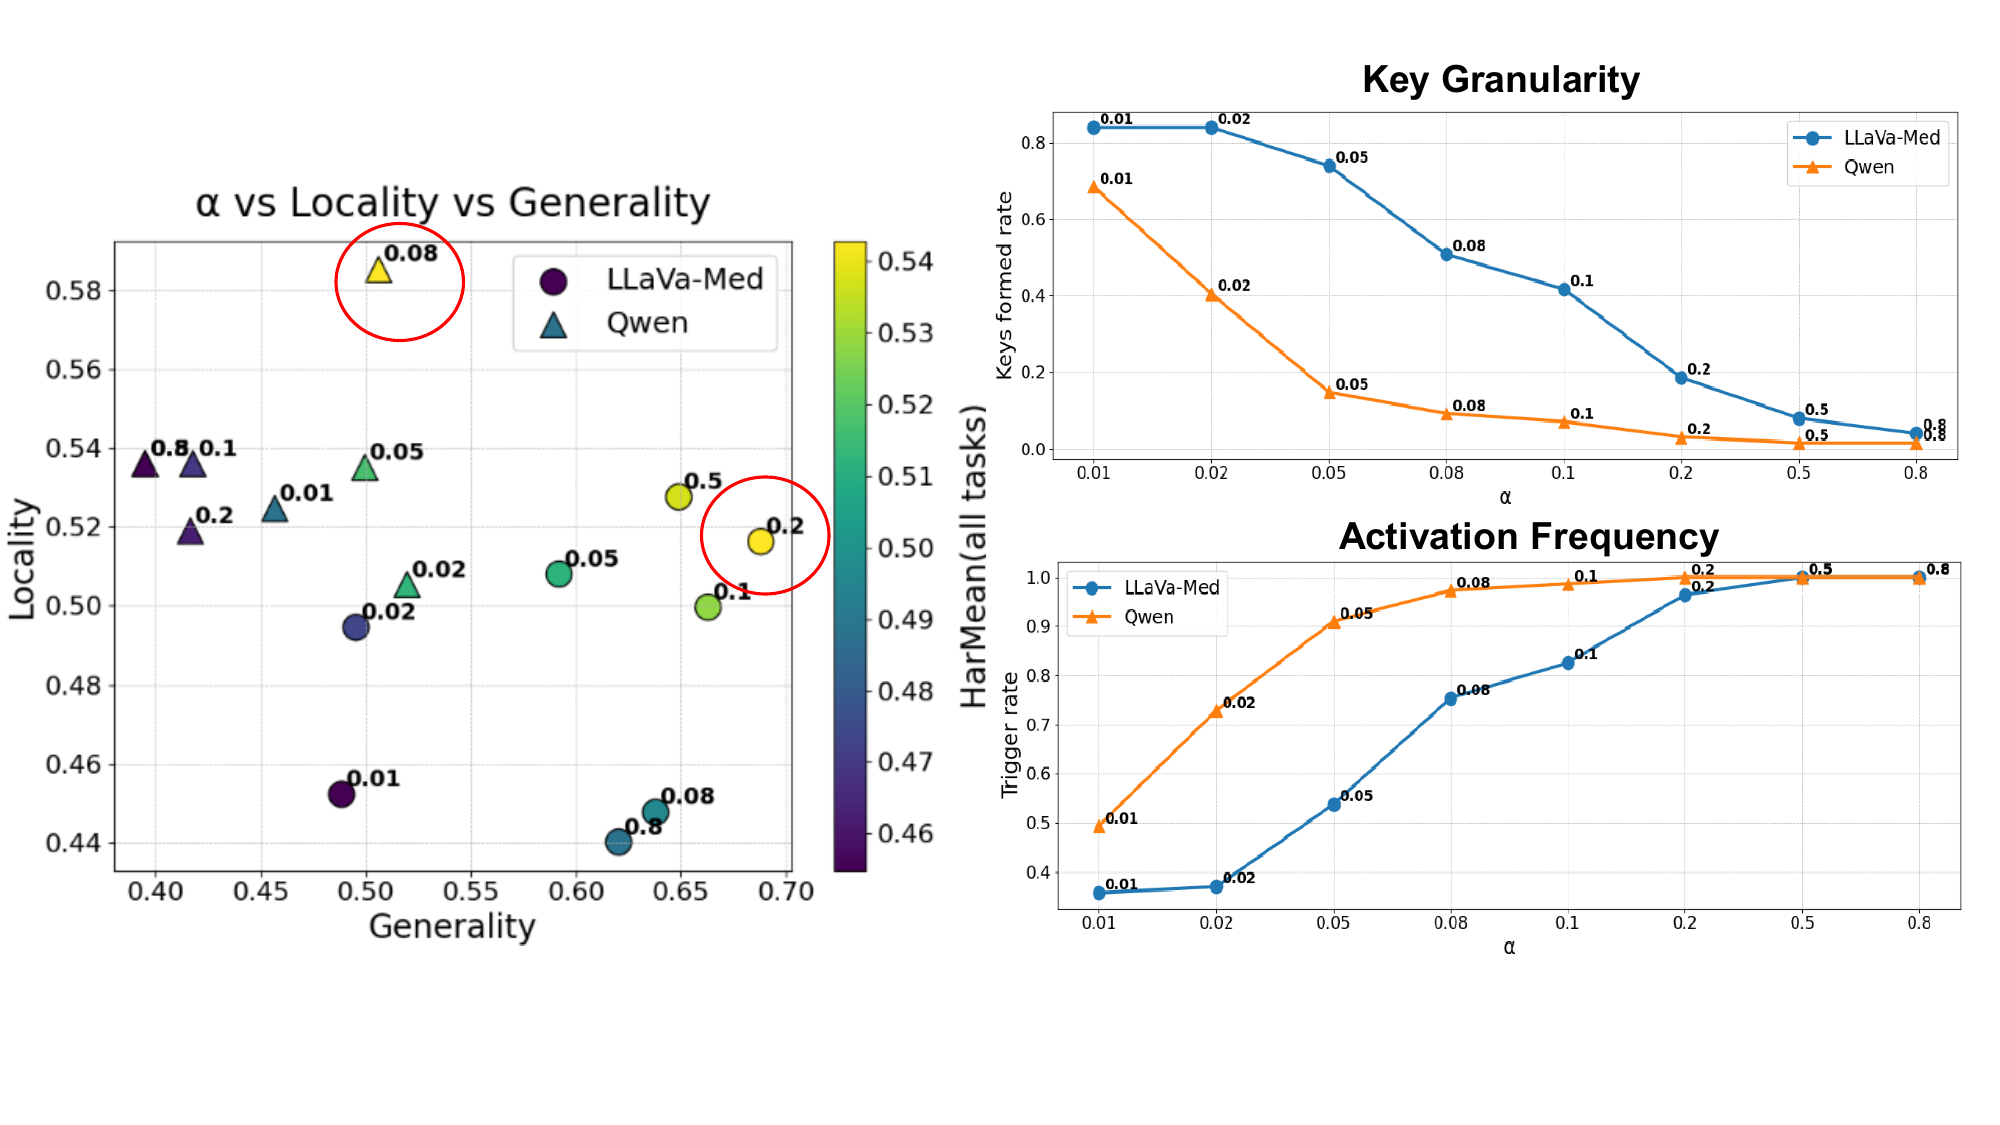
Memory-based editors depend strongly on the activation radius. A radius that works well for one VLM backbone can under-activate or over-merge edits for another backbone.
Repository Structure
The release is organized into benchmark task files, metadata, editing method implementations, and documentation.
| Folder / File | Description |
|---|---|
tasks/ |
Task-level benchmark files and evaluation instances. |
metadata/ |
Processed metadata, clinical attributes, and grouping information. |
Edit_Methods/ |
Editing method implementations and experiment scripts. |
README.md |
Main repository documentation. |
DATA_AVAILABILITY_AND_RELEASE_PLAN.md |
Instructions for obtaining original source datasets and reconstructing benchmark files. |
TASK_DEFINITIONS.md |
Formal task definitions and evaluation protocol. |
Citation
If you use M3Bench in your research, please cite our paper:
@inproceedings{m3bench2026,
  title     = {Evaluating and Understanding Model Editing for Medical Vision-Language Models},
  author    = {Zhu, Guli and Wu, Chenwei and Shen, Liyue},
  booktitle = {Proceedings of the European Conference on Computer Vision (ECCV)},
  year      = {2026}
}